Home›Treatments›Fully ablative CO₂ laser
Treatment
Fully ablative CO₂ laser resurfacing
The strongest single resurfacing treatment in dermatology. Instead of treating the skin in columns, the laser removes the entire damaged surface evenly, and new skin grows back over the following week to ten days. One treatment, a real recovery, and a result that fractional lasers need several sessions to approach.
What it is
A CO₂ laser at 10,600 nm vaporises water in the skin. In fully ablative mode it is delivered across the entire treated area instead of in a grid, so the whole epidermis and a set depth of dermis are removed in one even pass.
New skin grows back from the hair follicles and oil glands that sit below that depth. Because nothing is left untreated, the result from a single treatment is greater than any fractional laser can give. The trade-off is a longer recovery that needs careful aftercare.
What brings you here?
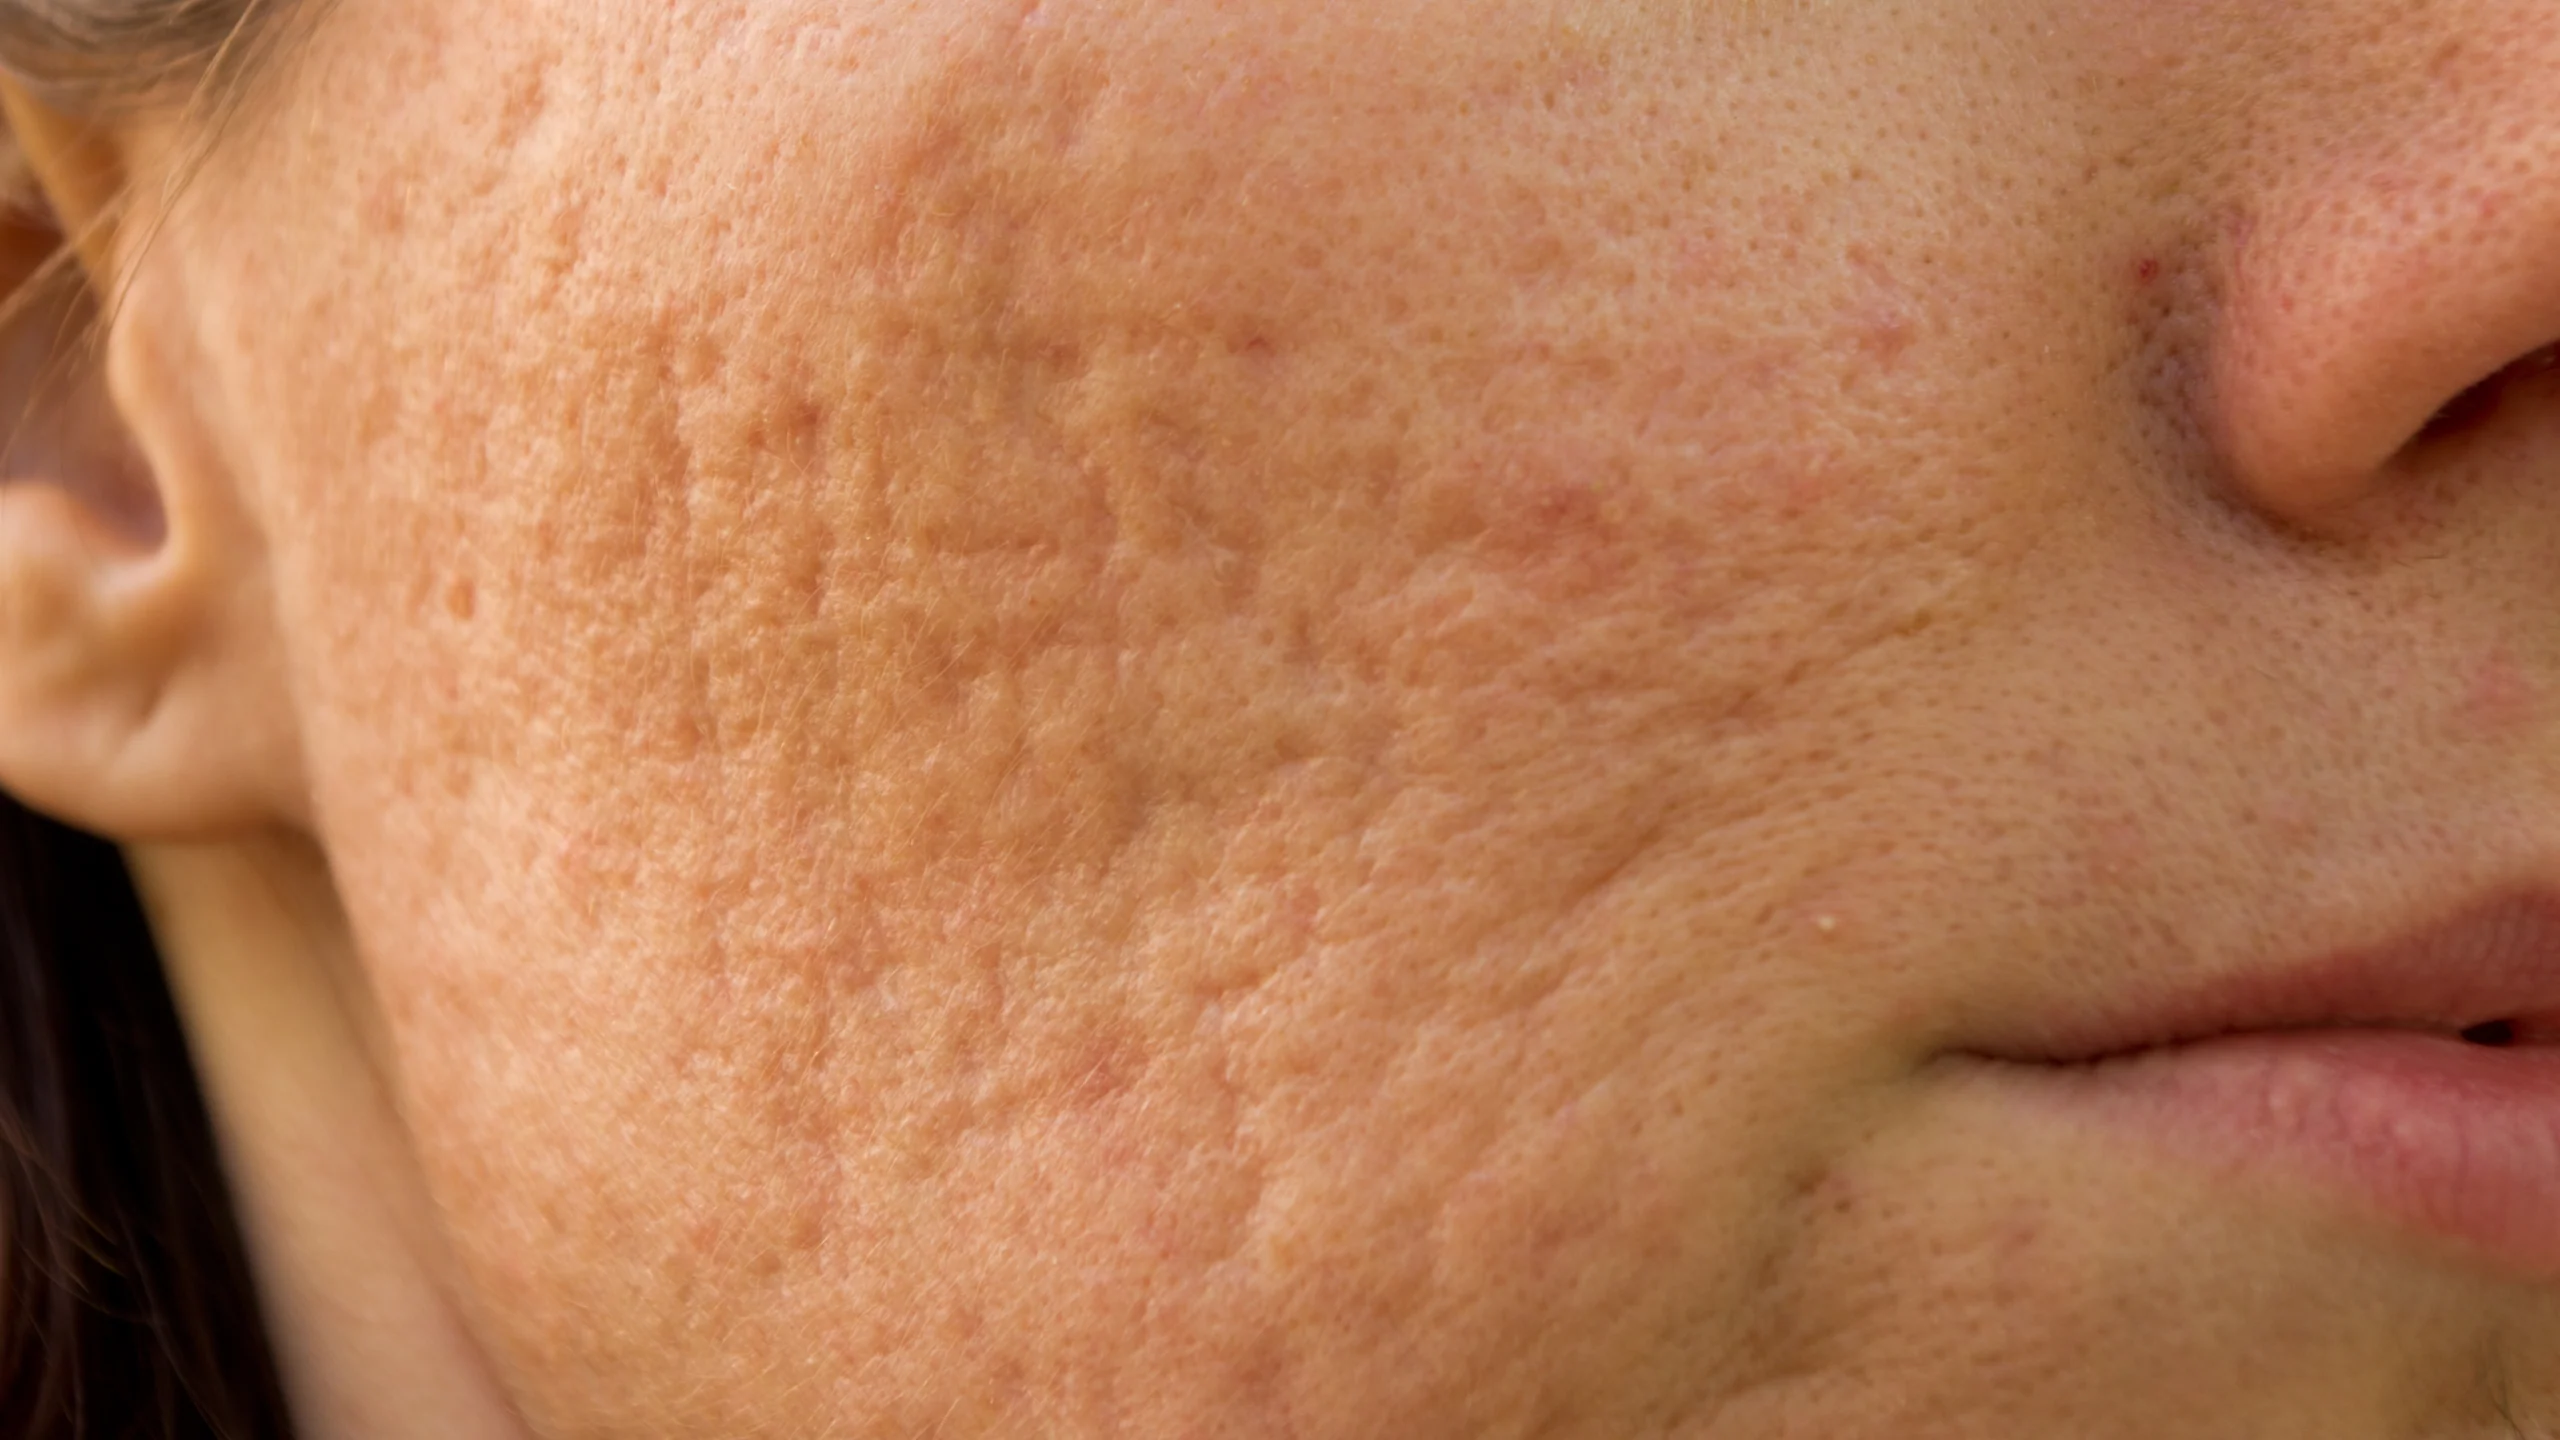 Acne scars →Rolling and boxcar scarring across the cheek
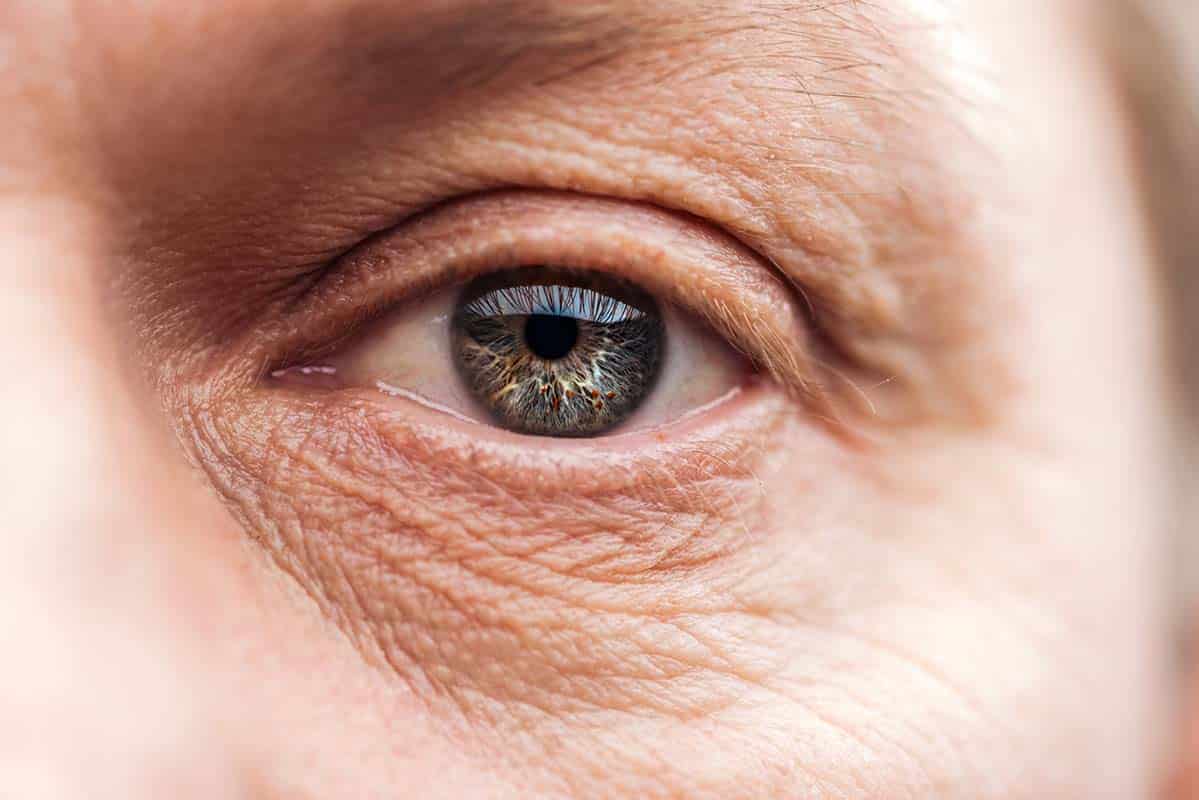 Eye rejuvenation →Crepey lid skin and crow’s feet
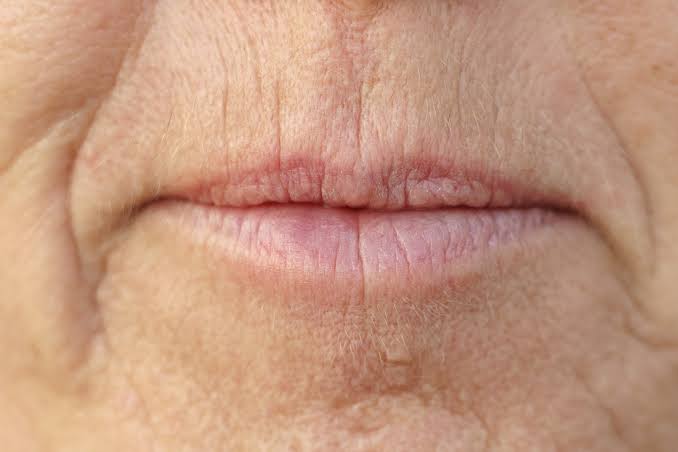 Smoker’s lines →Deep vertical perioral lines
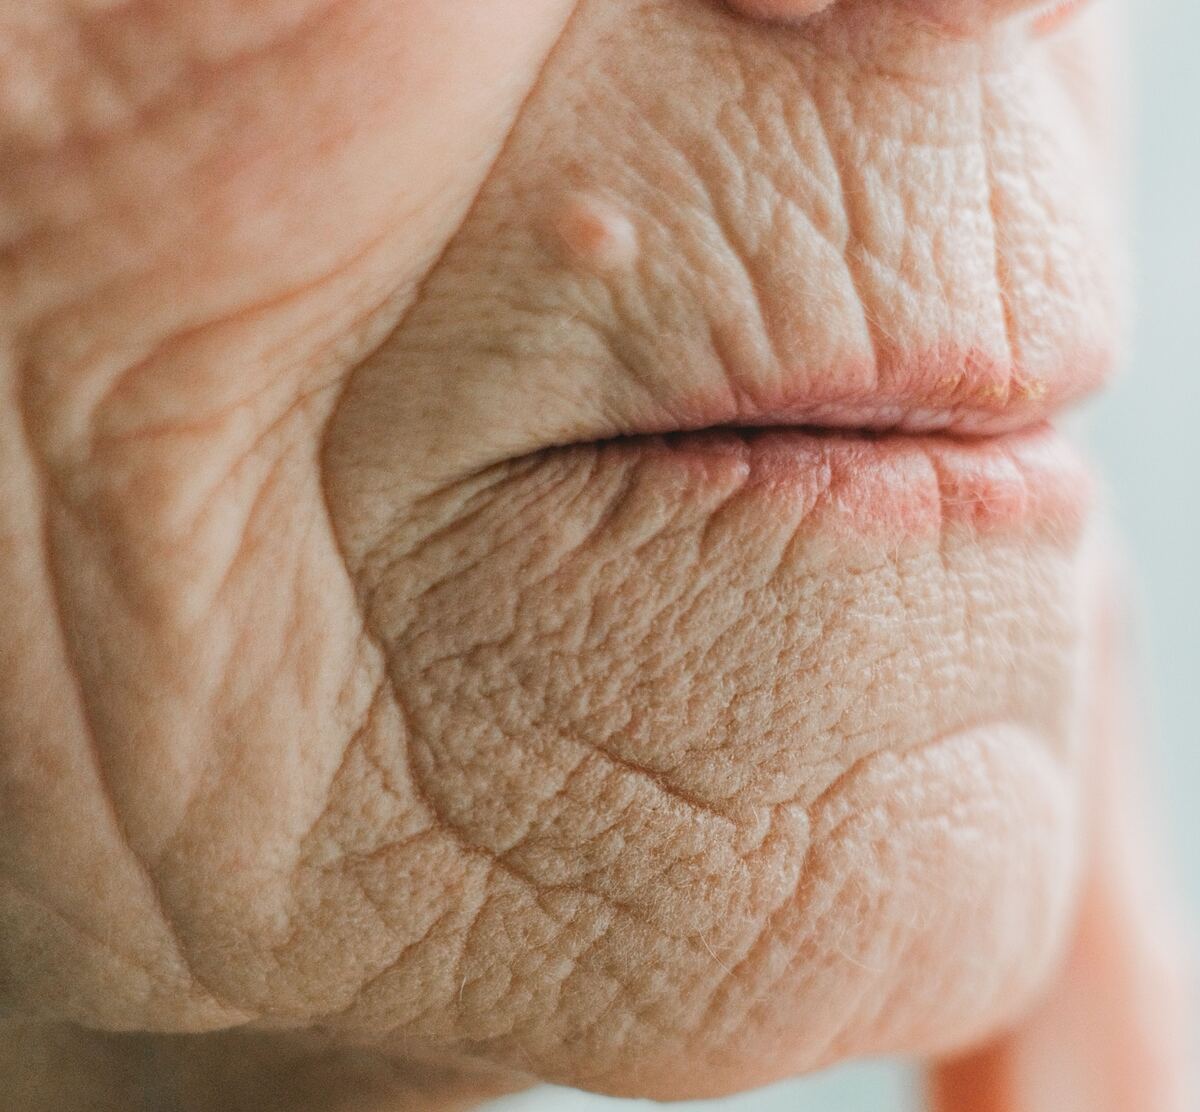 Wrinkles and skin laxity →Etched lines and laxity of the lower face
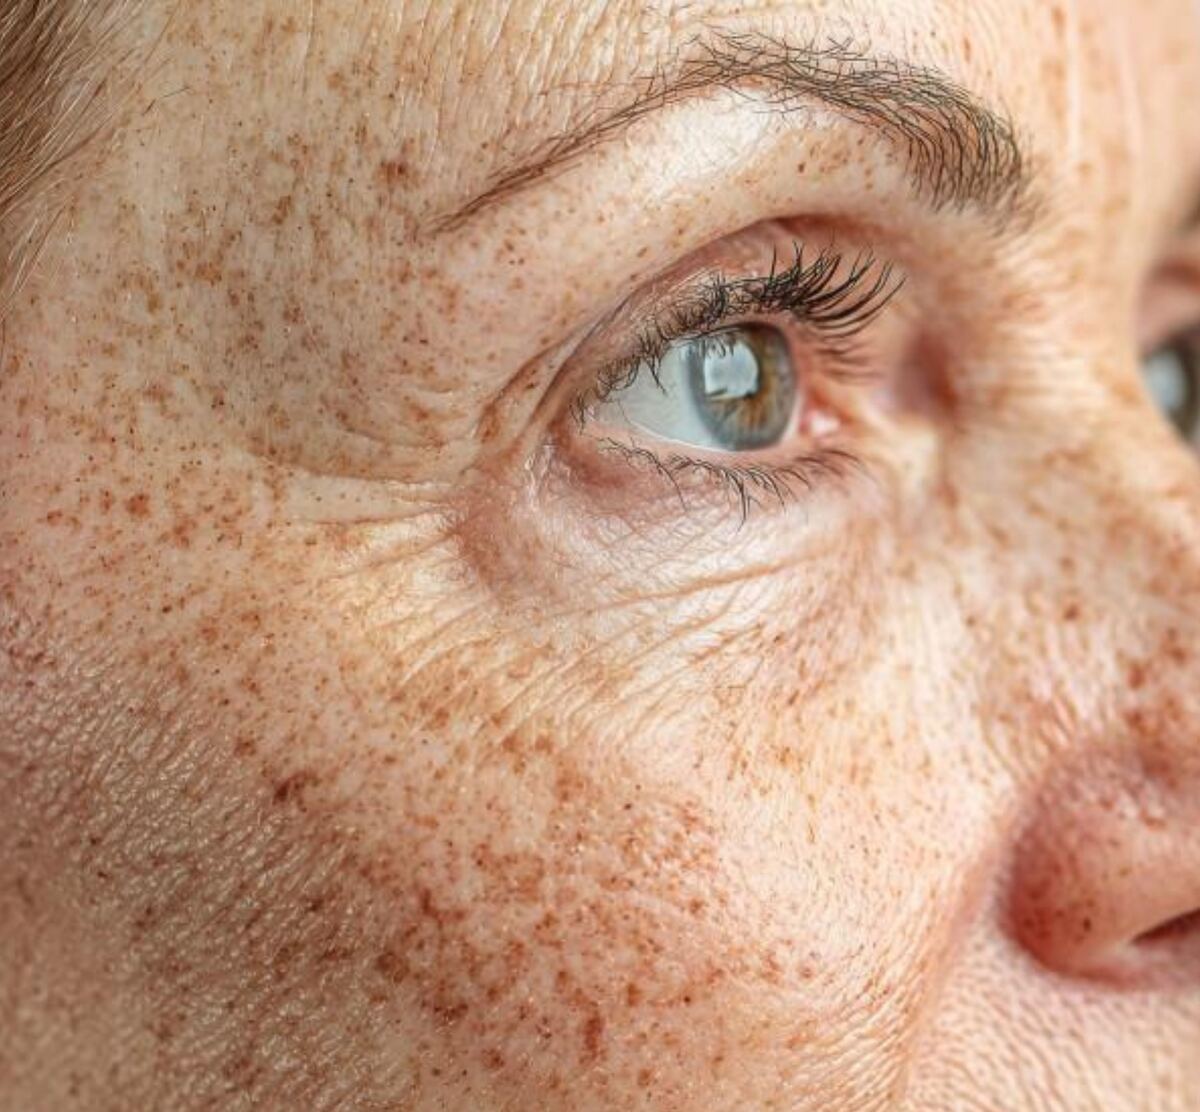 Sun damage →Chronic sun damage with freckling
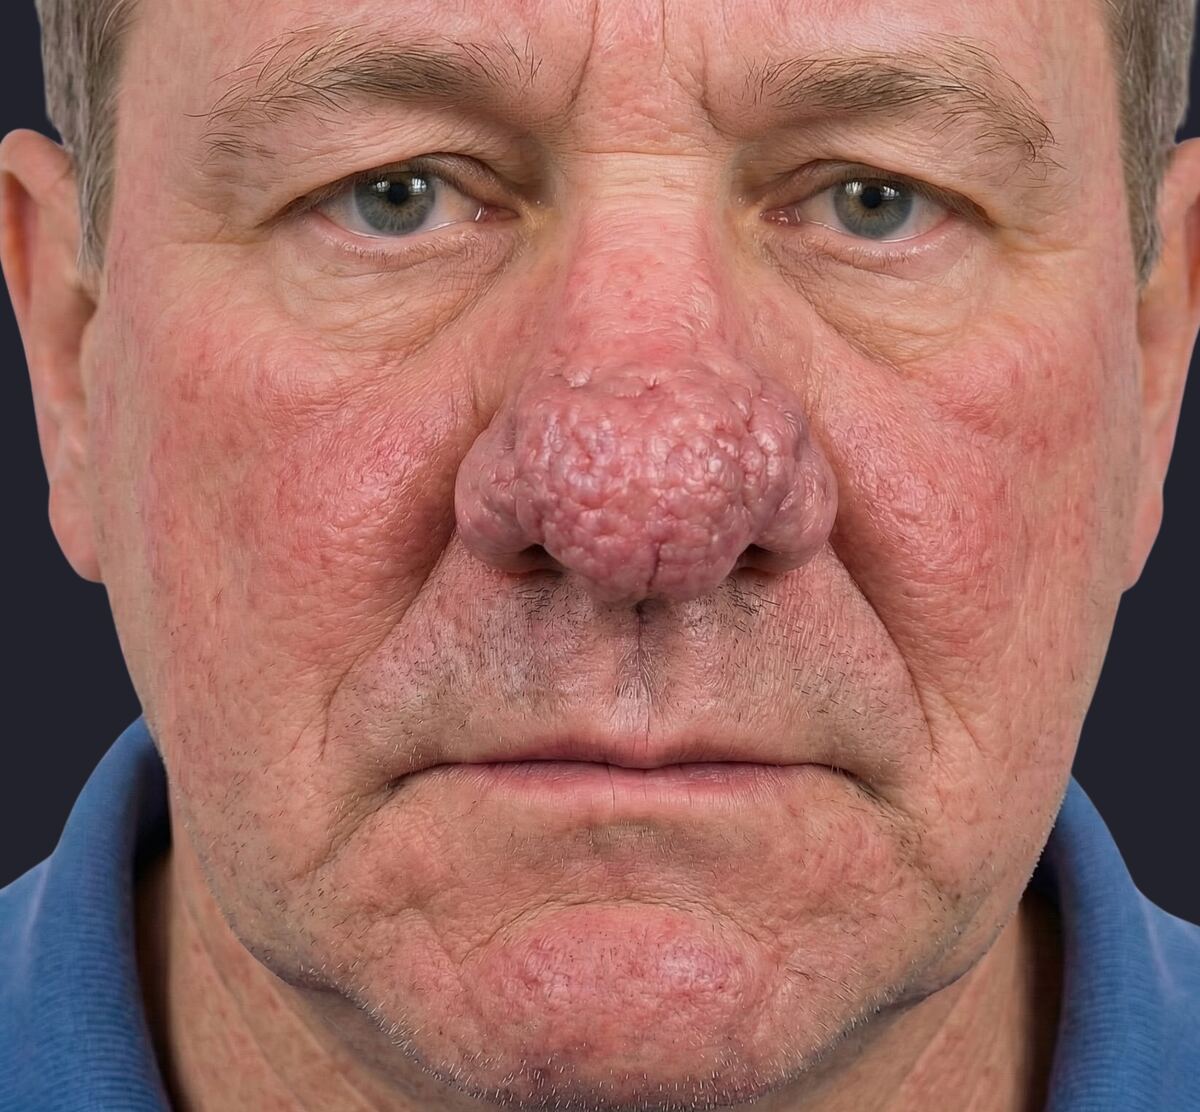 Rhinophyma →Thickened nose skin from rosacea
Acne scars
For widespread rolling and boxcar scarring in fair skin, fully ablative resurfacing gives the largest improvement available from a single laser treatment. The whole surface is removed to an even depth, the scar edges are taken down with it, and the skin re-forms across a flatter plane.
It is often the last step of a scar plan rather than the first. Deep narrow scars are treated with TCA CROSS beforehand, tethered scars are released with subcision, and the full resurfacing then evens out what remains.
What it will not do: CO₂ lasers treat scars that sit in layer 1 of the skin, the dermis. They do not replace fat, and fat loss sits beneath many deeper rolling atrophic scars. Those need soft tissue injectables as well as the laser.
Eye rejuvenation
Lower eyelid skin that has become thin, creased and crepey responds to full resurfacing better than to any fractional treatment. Removing the surface and heating the dermis beneath tightens the lid skin and softens the fine crinkling that makeup settles into.
This is precision work. Metal corneal shields protect the eyes, the settings are adjusted for the thinnest skin on the body, and the treatment is feathered out to the cheek so there is no visible border.
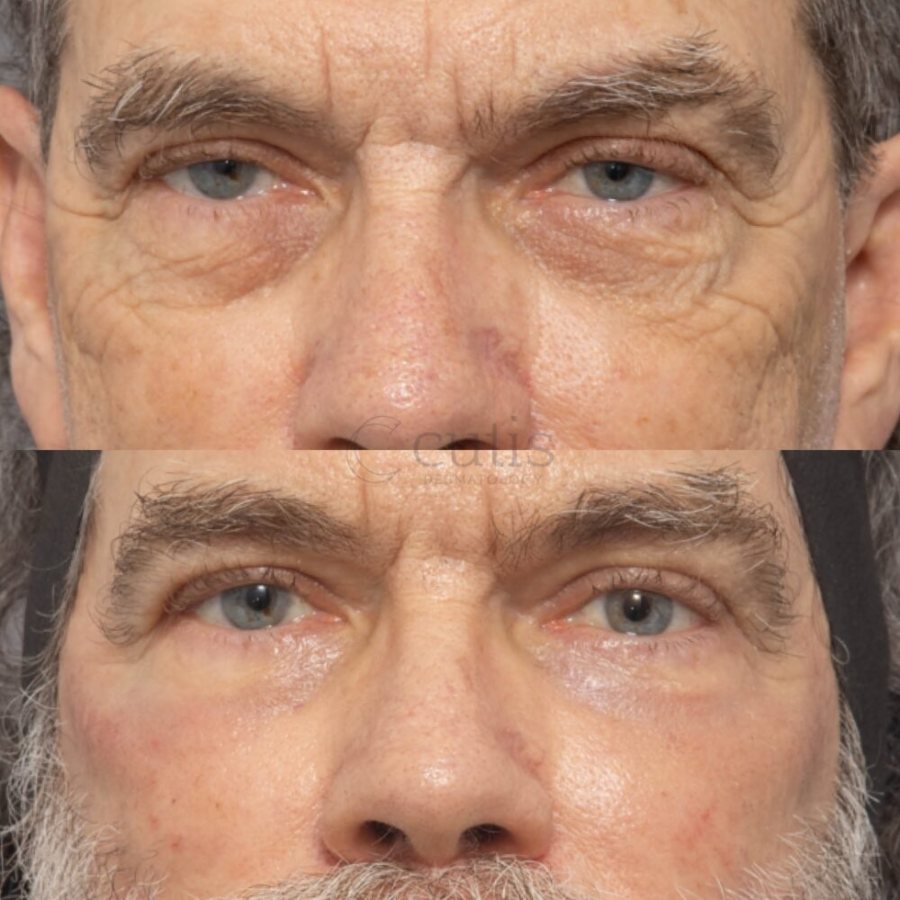 BeforeAfter
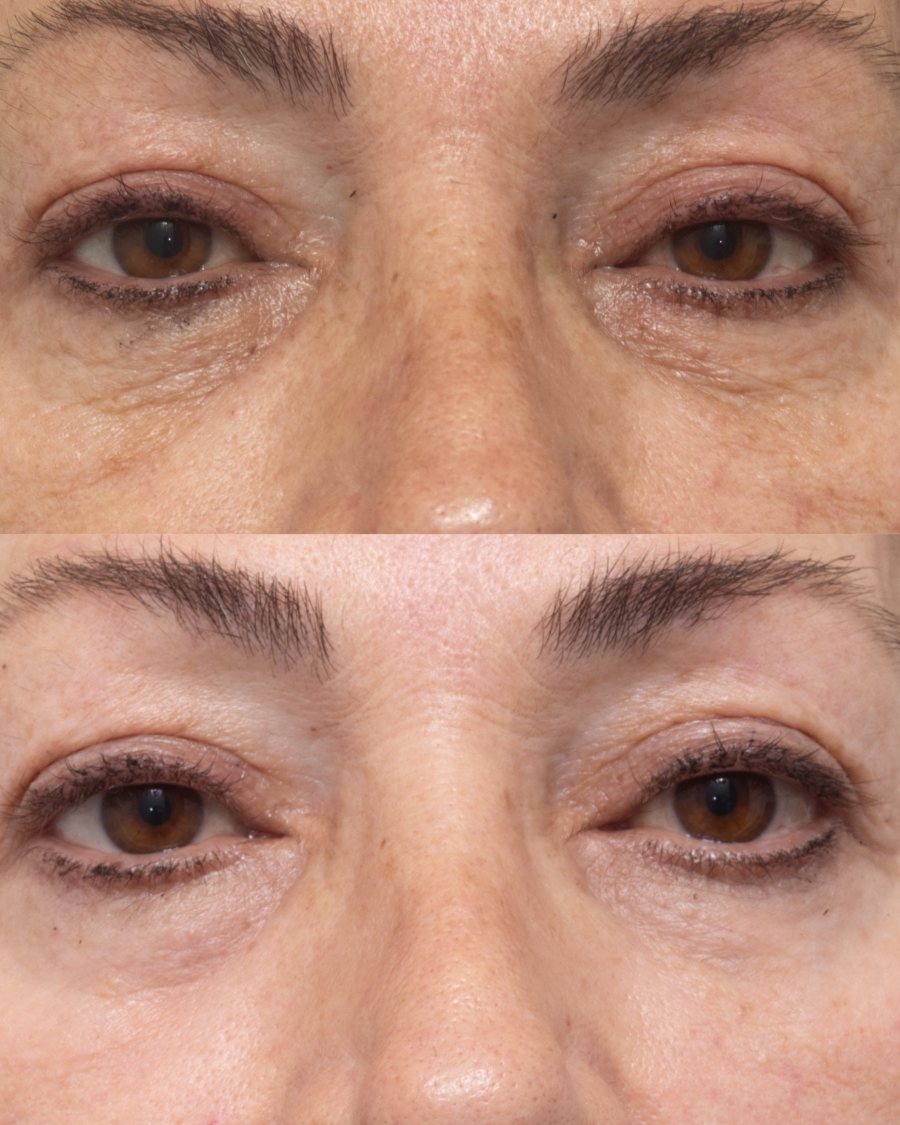 BeforeAfter
What it will not do: remove eye bags or excess lid skin. If tissue needs to come away, that is blepharoplasty. Resurfacing improves the skin that sits on top.
- Under-eye concerns →
- Neurotoxin →
Smoker’s lines
Deep vertical lines above and below the lips are where fully ablative resurfacing performs best. These lines are etched into thin, sun-damaged skin. Filler plumps the lip but leaves the lines, and fractional lasers only soften them. A full resurfacing takes the surface down evenly and lets it re-form without the creases.
The area around the mouth is small, so it is often treated on its own. You get the strongest result for this problem in a shorter procedure with a contained recovery.
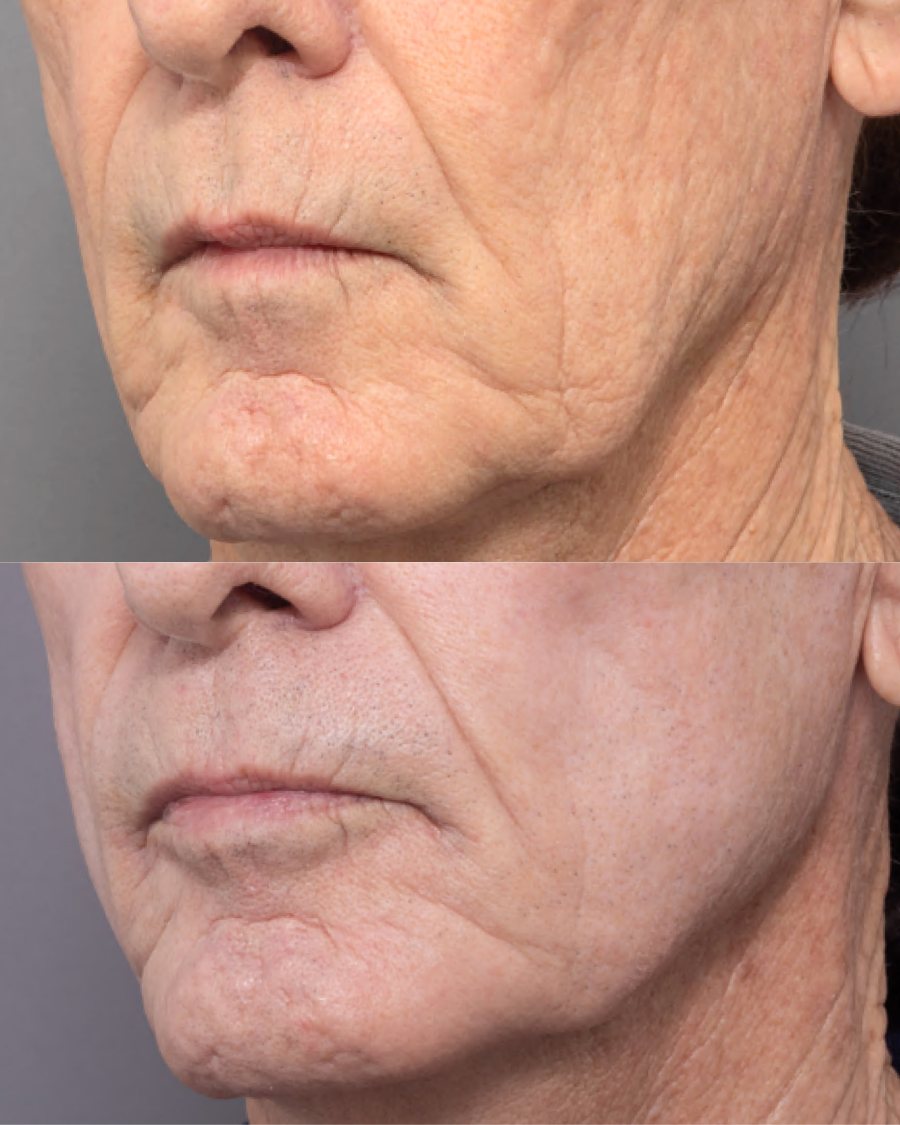 BeforeAfter
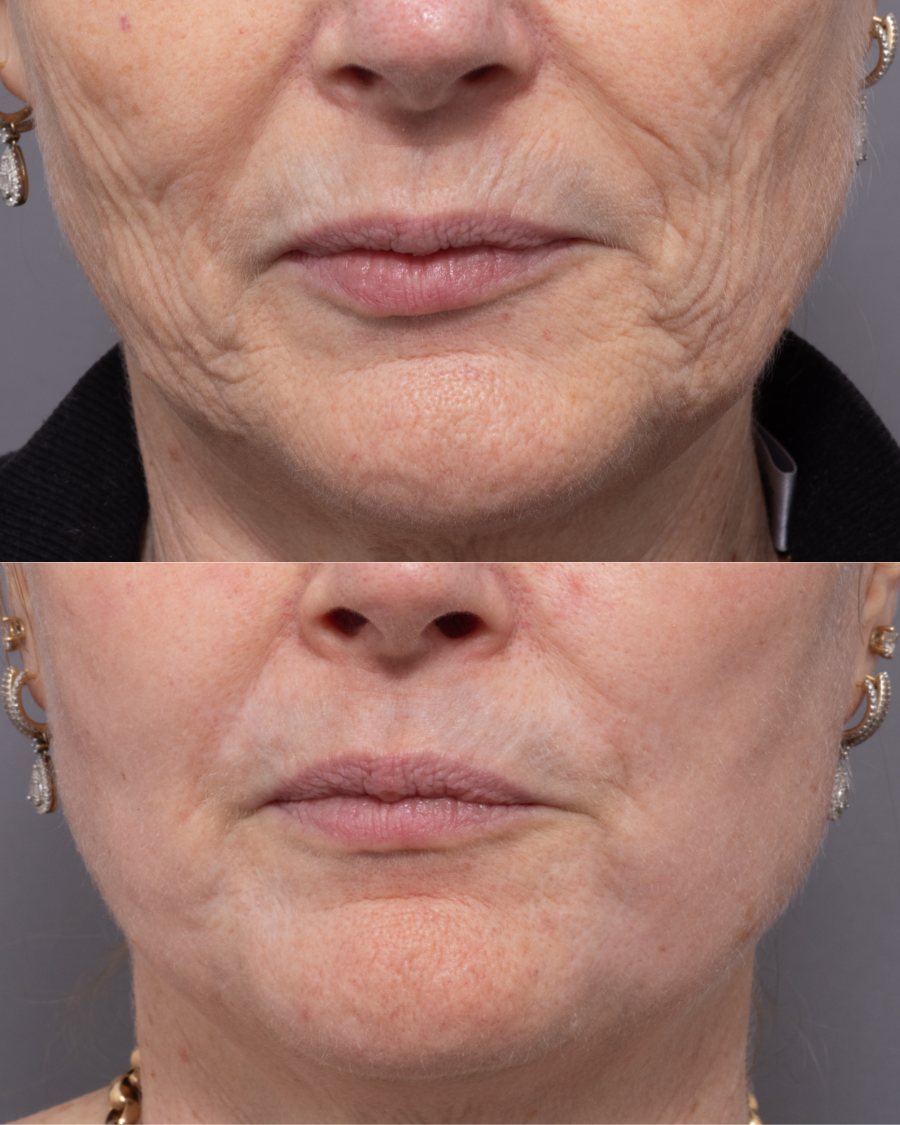 BeforeAfter
What it will not do: work while you are still smoking, or add volume to the lip. Volume is a separate conversation, best had once the skin has healed.
- Lip lines →
- Neurotoxin →
Wrinkles and skin laxity
Fully ablative resurfacing treats lines that are still there when your face is completely still, and it tightens skin more than any fractional treatment. Collagen contracts at the time of treatment, and new collagen keeps forming for six months or more afterwards.
It changes the quality of the skin, not where it sits. Skin that has dropped and needs repositioning is a surgical question. I will tell you so rather than recommend a resurfacing that cannot lift it.
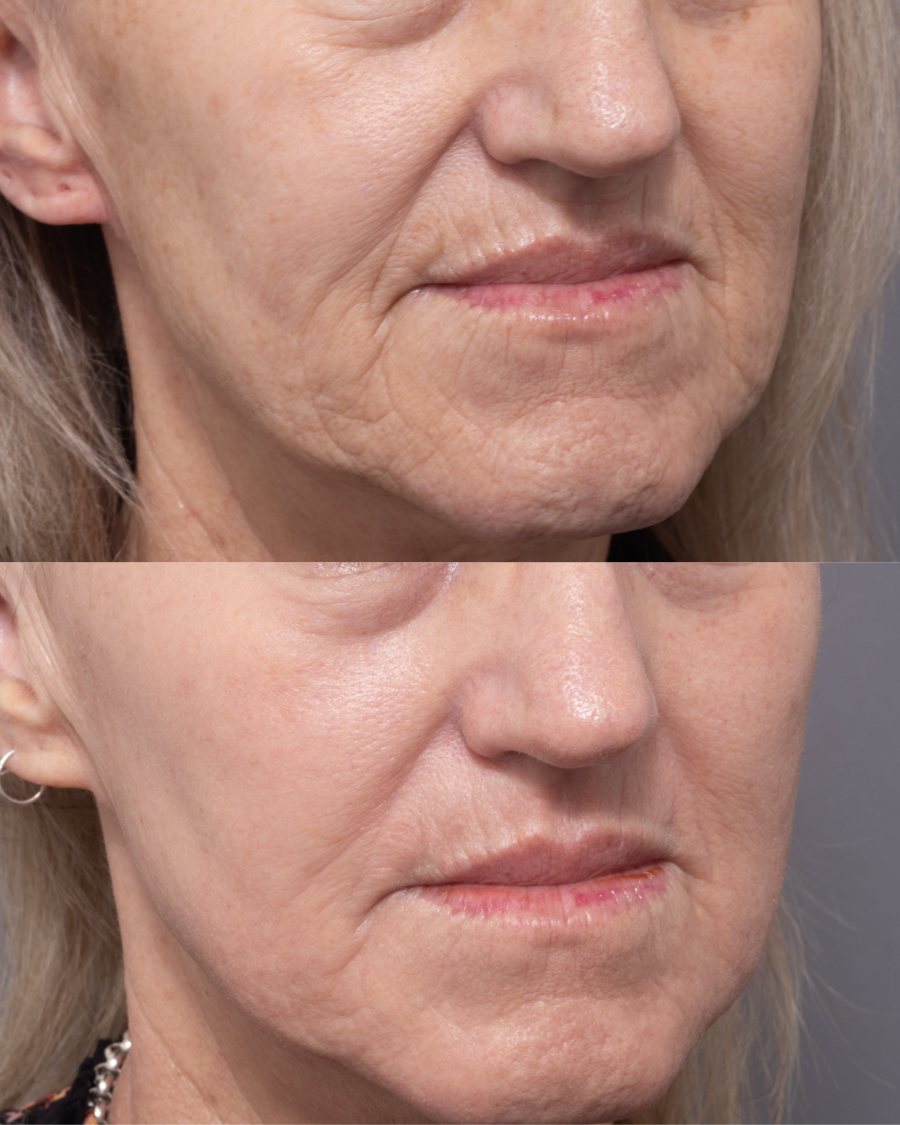 BeforeAfter
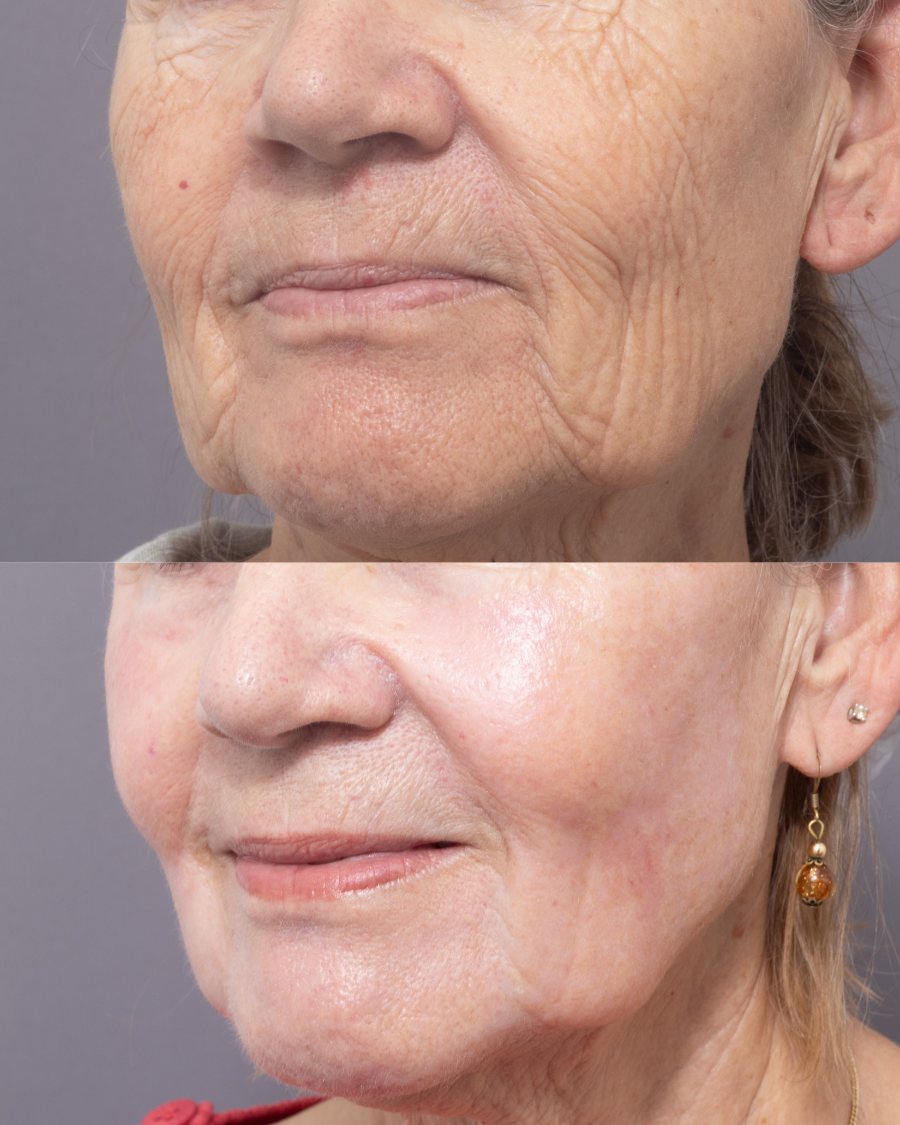 BeforeAfter
What it will not do: replace a facelift, or treat lines caused by movement. Those are muscle lines and respond to neurotoxin. The laser also does not restore lost fat in the superficial and deep fat pads; soft tissue injectables do.
- Wrinkles →
- Skin laxity →
- Neurotoxin →
Sun damage
Years of Australian sun leave mottled pigment, rough texture, fine lines and scattered pre-cancerous change. Full resurfacing replaces the entire damaged surface in a single treatment, and takes much of the freckling and many of the sunspots with it.
For people with widespread actinic damage it is field treatment as well as rejuvenation. Resetting the whole surface can reduce the number of new lesions over the following years, and in some cases a Medicare rebate may apply.
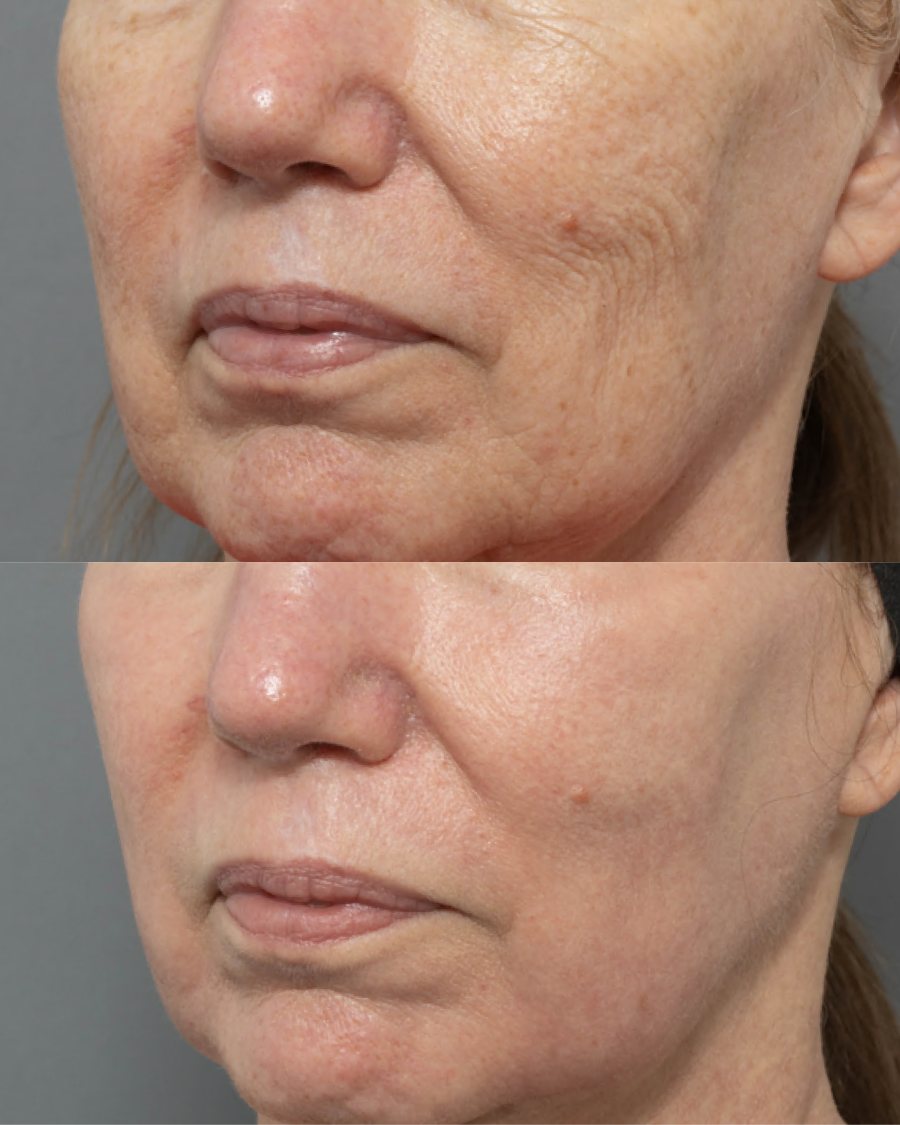 BeforeAfter
What it will not do: clear melasma, or protect you from future sun. Melasma can flare after resurfacing, and new damage starts again from the day you stop wearing sunscreen.
- Sun damage →
- Skin cancer →
- Fractional CO₂ laser →
Rhinophyma
Rhinophyma is thickened, enlarged skin on the nose from long-standing rosacea. Fully ablative resurfacing removes the excess tissue layer by layer, so the nose can be recontoured back towards its natural shape.
What it will not do: treat the redness and flushing of rosacea. That is a job for vascular laser and medical treatment.
Everything below applies to the above conditions
The procedure and the recovery are the same whichever concern brought you here. Only the depth and the area change.
What happens on the day
- Preparation, weeks before
Pigment-preparing topicals for fair-to-medium skin, and an antiviral started before treatment to prevent cold sores.
- Photographs and marking
Standard photographs, then the treatment areas and feathering borders are marked.
- Anaesthetic
Nerve blocks with sedation for smaller areas. Full-face treatment is done under general anaesthetic with an anaesthetist.
- The treatment
The UltraPulse is passed evenly across each area and the edges are blended into untreated skin so there is no line.
- Immediately after
Thick occlusive ointment, cool compresses and written aftercare. You go home the same day and need someone with you that night.
Recovery, at a glance
My team and I will advise you of your recovery. With fully ablative resurfacing, plan for 1–2 weeks away from work and social commitments, and a further month or two of redness. Settings matter, and so does aftercare.
Best combined with
Fully ablative laser resurfacing is best combined with collagen stimulators. Collagen-stimulating injections act synergistically with your immune system to further boost collagen production.
These collagen stimulators are placed between 4 and 12 weeks after your resurfacing procedure. They are placed in strategic areas, such as areas of scarring, and in key areas to help improve your skin’s turgor to help lift and contract key areas, such as the jowls, smile lines and brow.
Depending on the amount of collagen we want to stimulate, between 1 and 3 injections are placed 8 to 12 weeks apart.
Risks
| Effect | Frequency | Notes |
|---|---|---|
| Swelling, weeping, crusting | Expected | The first week. This is healing, not a complication. |
| Prolonged redness | Expected | Up to 3 months is normal. May persist for 6 months or longer depending on settings. |
| Temporary darkening | Common | Weeks four to eight, more likely with sun exposure. Treated with topicals. |
| Acne or milia | Common | From ointment during healing. Settles with a change of regimen. |
| Cold sore flare | Uncommon | Prevented with antivirals started before treatment. |
| Infection | Uncommon | Bacterial, viral or fungal. Reviewed closely in the first week and treated promptly. |
| Loss of pigment | Rare | Can appear months to years later. This is why skin type selection matters. |
| Scarring | Rare | Most often linked to infection or treating beyond the face. |
Who is and isn't a candidate
Best suited to fair skin with significant scarring, sun damage or etched lines, in people who can take two weeks of recovery and commit to strict sun protection afterwards.
Tell me beforehand if you have a history of cold sores, as treatment has the potential to bring them out. A simple antiviral treatment is the solution.
Also tell me if you are pregnant, have used oral retinoid therapy in the last six months, form keloid scars, have melasma, have a tan, or have olive or darker skin.
Don't come in for treatment in the month before a big event. That is common sense.
Common questions
How much does it cost?
Who performs it?
How is this different from fractional CO₂?
How much downtime is there?
How many sessions will I need?
Is it suitable for darker skin?
Does it hurt?
How long do the results last?

Why I use one laser for this
Dr Davin Lim · Dermatologist · The Skin Hospital, Sydney — Laser, Procedural and Anaesthetic Division
For fractional work I keep several CO₂ platforms, because matching the machine to the problem keeps downtime in proportion to the result. Fully ablative resurfacing is different. Here the one thing that matters is removing tissue cleanly to a precise, even depth with as little heat left behind as possible, and one laser does that better than the rest.
The laser I use
 LumenisUltraPulseHigh peak power in very short pulses. It vaporises tissue before heat can spread, so each pass removes a predictable layer with minimal thermal damage beneath it.
Why clean ablation matters
Most complications of full resurfacing, such as delayed pigment loss, prolonged redness and scarring, are driven by heat left behind rather than by the depth of tissue removed. A laser that ablates cleanly lets me reach the depth a scar or deep line needs while keeping the healing predictable.
Balanced aesthetics
Full resurfacing is exceptional for skin quality: texture, etched lines, sun damage and scarring. It does nothing for lost fat in the superficial and deep fat pads, and it does not lift tissue that has descended. I plan it as one part of a balanced approach. Soft tissue and collagen-stimulating injectables restore structure, neurotoxin softens movement, and the laser does the one job it does best. Used together at modest doses, the face looks well rather than treated.
When I recommend against it
Olive or darker skin, melasma, a recent tan, or anyone who cannot take two weeks of recovery. In those situations fractional CO₂ gets to a similar place over more sessions, with far less risk.
— Dr Davin Lim, Consultant Dermatologist
Conditions this treats
Related treatments
Book a consultation
Assessment, photographs and a written plan, including whether full or fractional resurfacing suits your skin.
Book a virtual consultationHave some questions?
Send a message and it will be answered personally. Form endpoint — to be wired in production
See the work before you book
Procedures, technique, before and afters, and the reasoning behind them — posted across three accounts, each with its own focus.