Is it melasma, or something that looks like it?
Clinical Pearls: Melasma Diagnosis & Differential Diagnosis
Several conditions produce brown patches on the face, they respond to completely different treatments, and treating the wrong one makes some of them worse. This is the table I use to tell them apart.
What we found
Melasma has a distinctive distribution.
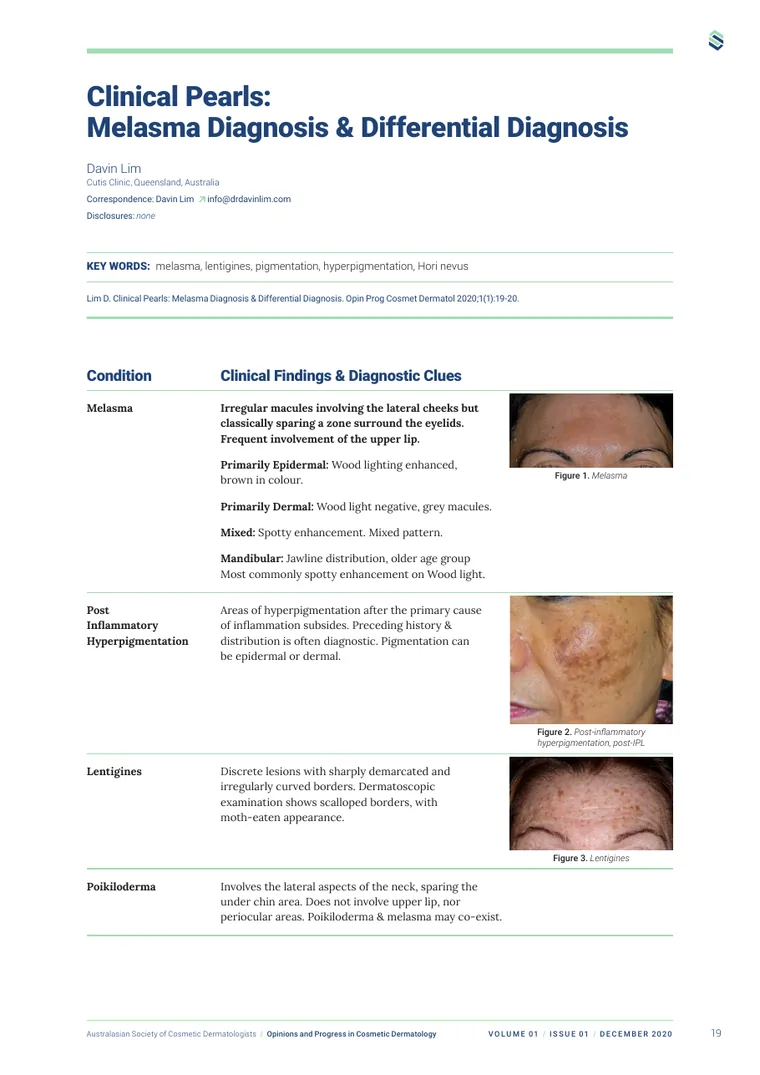
Irregular patches on the outer cheeks, classically sparing a zone around the eyelids, and frequently involving the upper lip. That eyelid-sparing pattern is one of the most useful single clues.
How deep the pigment sits changes what will work.
Under a Wood's lamp, epidermal melasma is enhanced and brown; dermal melasma is Wood's-light negative and grey; mixed shows patchy enhancement. Mandibular melasma sits along the jawline in an older age group.
Post-inflammatory pigment is diagnosed by its history.
Pigment appearing where inflammation has been — acne, a rash, a procedure. The preceding event and the distribution usually give it away, and like melasma it can be epidermal or dermal.
Hori naevus is the one most often mistaken for melasma.
Slate-brown or blue-grey discrete macules around the eyes, which do not affect the upper lip. On dermatoscopy, brown-to-grey structureless areas signify dermal pigment, with no increase in visible vessels. It can coexist with melasma, which is what makes it difficult.
Lentigines and freckles have edges melasma does not.
Lentigines are discrete with sharply demarcated, irregularly curved borders and a moth-eaten dermatoscopic edge. Freckles involve the nose, spare the upper lip, and fluctuate with sun exposure.
Poikiloderma, demarcation lines and acanthosis nigricans complete the list.
Poikiloderma takes the sides of the neck and spares under the chin. Pigmentary demarcation lines run sharply from the outer orbit and start in adolescence. Acanthosis nigricans is velvety, favours flexural areas and darker skin, and can signal insulin resistance.
Drug-induced pigment is a history question.
Minocycline and non-steroidal anti-inflammatories are the usual culprits, and the pigment may localise to scars.
What this means for you
The upper lip is a useful landmark
Melasma frequently involves it. Hori naevus and freckles do not. It is a small observation that separates two conditions needing very different treatment.
A Wood's lamp costs almost nothing and changes the plan
Whether the pigment is epidermal or dermal is the single biggest determinant of how well it will respond and how long it will take.
Bring your history, not just your face
Post-inflammatory pigment, drug-induced pigment and melasma can look alike. What happened before the pigment appeared is often the piece that settles it.
Two things can be true at once
Hori naevus and dermal melasma coexist often enough that assuming one excludes the other is a common way to end up treating half the problem.
Why this matters
Facial pigmentation gets treated as though it were one condition. It is not, and the distinction is not academic: aggressive laser on melasma makes it worse, while the same laser on a Hori naevus is appropriate treatment.
This piece is a clinician's reference table — condition by condition, the findings and the diagnostic clues that separate them. It is written for dermatologists, but the underlying point matters just as much to a patient: if you have been treated for melasma without improvement, the first question is whether it is melasma at all.
Why it matters to you
A treatment plan built on the wrong diagnosis does not simply fail. In pigmentation it often makes things darker, and in melasma specifically the wrong laser at the wrong setting can set you back a year.
What this study cannot tell you
Every study has a boundary, and it is fairer to state it than to leave you to guess.
- This is a clinical reference table, not a study. It reports how these conditions are distinguished in practice, not how accurately.
- It is written for clinicians, and assumes access to a Wood's lamp and a dermatoscope.
- No diagnostic accuracy figures are offered, because none were measured.
- Photographs illustrate typical presentations. Real faces frequently carry more than one of these conditions at once.
Questions people actually ask
How do I know if I have melasma or something else?
Distribution and history do most of the work. Melasma favours the outer cheeks, classically spares a zone around the eyelids and frequently involves the upper lip.
A Hori naevus produces discrete blue-grey macules around the eyes and does not affect the upper lip. Freckles involve the nose and fluctuate with the seasons. Pigment that appeared where a rash or breakout used to be is post-inflammatory.
What is a Wood's lamp used for?
It shows how deep the pigment sits. Epidermal pigment — nearer the surface — becomes more obvious under the lamp and looks brown. Dermal pigment does not enhance and looks grey.
That distinction predicts how well treatment will work and how long it will take, which is why it is worth doing before anything is prescribed.
What is Hori naevus?
A melanocytic naevus producing slate-brown or blue-grey discrete macules around the eye area. The pigment sits deep in the skin.
It is frequently mistaken for melasma, and the two can coexist. The useful distinguishing feature is the upper lip: Hori naevus does not involve it, and melasma often does.
Cite this paper
Lim D. Clinical Pearls: Melasma Diagnosis & Differential Diagnosis. Opinions and Progress in Cosmetic Dermatology. 2020;1(1):19–20.
Related reading
Want this assessed properly?
A virtual consultation gives you a written report and a plan before we speak.
Published 2020 · Summary written and reviewed by Dr Davin Lim, FACD · General information, not personal medical advice.
Have some questions?
Send a message and it will be answered personally. Form endpoint — to be wired in production